

This is the second post in a series of weekly primers on what Australian medical students learn in psychiatry. “/” indicates content taught within the medical curriculum; “\” indicates content beyond. Introductory post here, post #1 on depression here.

\ The psyche moulds art; art shapes psychiatry.
Depression seems to bring a sombre, realist lens to a creative’s mind. David Foster Wallace and Sylvia Plath are two modern examples immortalised into literary canon: The Bell Jar depicts a woman’s disillusionment and descent into suicide, while Infinite Jest critiques modern society’s culture of addiction. Both were pushed into suicide through their machinations. Both were prodding the cultural zeitgeist of the status quo.
Mania, perhaps, brings a fevered, radiant filter. Vincent van Gogh painted his pièce de résistance, The Starry Night, in the mental asylum Saint-Paul de Mausole. His voluntary submission was precipitated by an episode of aural self-mutilation, as depicted in his self-portrait.
Through his letters to loved ones, and asylum documentation, we glean a picture of his mental status throughout these years. He suffered from an episodic condition, one which included “intolerable hallucinations”, and a persistent “undercurrent of vague sadness” that could “easily relapse into a state of overexcitement”. These were supplemented by seizures, poor digestion, insomnia, amongst other symptoms.
Across the 20th and 21st centuries, clinicians have speculated what ailment troubled van Gogh; in modern neuropsychiatry, there are two prevalent hypotheses. Blumer (2002) presents the neurologic case for temporal lobe epilepsy, whilst Nolen et al. (2020) presents the modern psychiatric account for Bipolar Disorder. Ultimately, there may have been some mixture of both.
This points to the common popular connection between Bipolar Disorder and creativity; that human elements of mood are crucial for artistic expression. This may be true - but undermines the suffering of individuals and their loved ones, who deal with the emotional and psychological harms of clinical mania. This is what the realm of psychiatry attempts to deal with.
/ DSM-V Symptomology of Mania
As with depression, there is also a medical student mnemonic for mania: DIGFAST. Distactability, Indiscretion, Grandiosity, Flight of ideas, increased Activity, lack of Sleep, Talkativeness.
The DSM-V stipulates that three or more symptoms, alongside an abnormal elevated mood nearly every day across a week, constitutes the criteria for a manic episode. In the functional caveat that this mood must also cause marked impairment, it also interestingly notes the presence of psychotic features.
The subcategorisation, of Bipolar I vs Bipolar II, is distinguished by the level of mania. Bipolar I disorder requires at least one manic episode - whereas Bipolar II is diagnosed through having at least one hypomanic episode and one major depressive episode. The key distinction in hypomania lies in that it requires at least 4 days, it does not cause functional impairment, and has no psychotic features.
Similar to dysthymic disorder (AKA Persistent Depressive Disorder/Depression for >2 years), there is also the manic equivalent of Cyclothymic Disorder. This holds a more chronic diagnosis, needing a 2-year history where there are both hypomanic and depressive symptoms, but do not meet the criteria for the episodes themselves. Further, in an attempt to add more specificity, mood diagnoses also have symptomology classifiers, such as having mixed features (refers to episodes which have at least 3 symptoms from the opposite pole).
Unlike the monoamine theory around depression, we are not given a simple model which accounts for mania - likely the topic of a Nobel Prize in the future. This is perhaps related to the complexity of Bipolar’s miracle drug, atomic element number 3.
/ Lithium and the Biology of Antimanics
Dr John Cade, to the great pride of Australian psychiatry, is credited with the discovery of lithium’s efficacy in Bipolar Disorder. In 1949, he published the widely cited Lithium salts in the treatment of psychotic excitement in the Australian Journal of Psychiatry. His surprising discovery was shocking even to him, noting “it may seem a long distance from lethargy in guinea-pigs to the excitement of psychotics”.
\ Aside: It is always fascinating to read the medical literature of the past - Lithium’s discovery was in fact first an investigation into the urine of manic patients, and after injections of lithium into guinea pigs, found a profoundly sedating effect. A dosage experiment on himself, and ten successful patient case reports later, he cautiously reports the powerful sedation of mania using these tablets, particularly as an alternative to the lobotomies of the time.
No drugs have surpassed Lithium for the acute treatment of mania in psychiatry, with the most recent meta-analysis reporting Lithium as an effective treatment for ⅔ of patients (Ulrichsen et al., 2023). Current treatment paradigms focus on two phases; acute management, and chronic prevention. Lithium is indicated in both, with new regimens including sodium valproate (also an antiepileptic) and other antipsychotics.
For instance, the RANZCP guidelines indicate use of sedation via antipsychotics (Aripiprazole, Asenapine, Risperidone, Quetiapine, Cariprazine) and benzodiazepines, whilst starting lithium or valproate. The long term prevention of mania regimens tend to include either lithium, valproate, lamotrigine alone, or if unsuccessful alongside an antipsychotic.
The side effects of lithium are particularly potent. Acute symptoms include the transient 3Ts of tiredness, tremor, and thirst, as well as somatic symptoms such as headache and nausea. Since lithium is eliminated through the kidneys and can accumulate in the thyroid, it can also cause renal disease and hyperthyroidism. This means the acute dosage of lithium needs to be carefully titrated alongside a battery of tests, aiming for a blood plasma concentration of 0.6- 0.8mmol/L.
However, despite our relative clinical understanding, the biology of lithium is much less clear. Even if flawed, antidepressants have some tractable claim on the monoamine hypothesis of depression with the main drug classes focusing on serotonin and noradrenaline. Lithium appears to act on too many systems - multiple neurotransmitter systems, second messengers, intracellular signalling… The figure certainly paints a complex, non-linear story of mood, which likely reflects something closer to a biological truth.
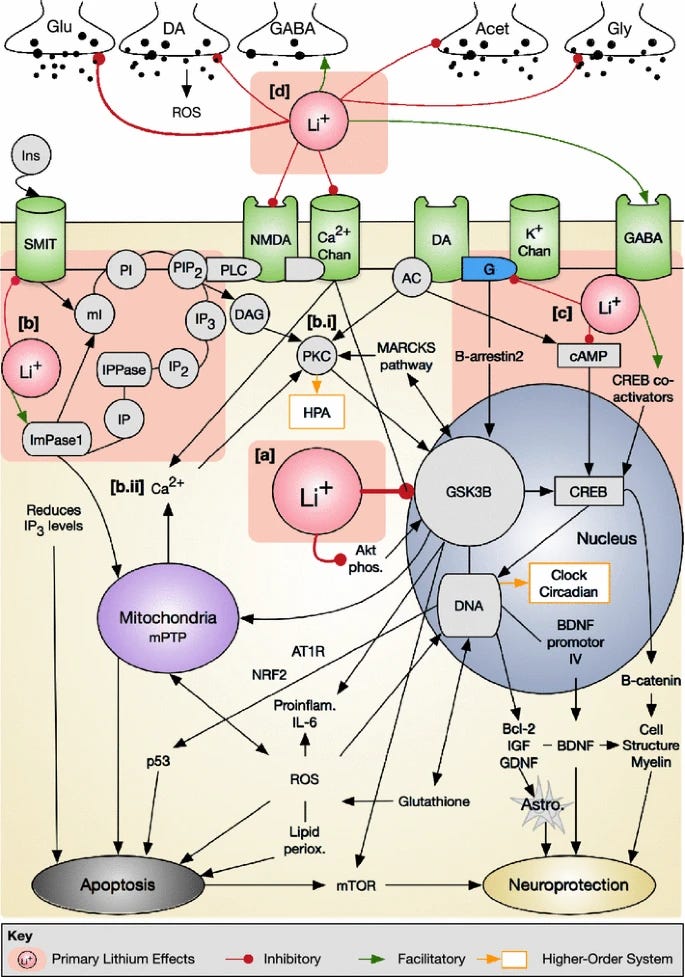
\ The biological approach continues to expand this figure - with newer models of Bipolar Disorder include other systems such as circadian rhythms, HPA axis, and stress response (Scaini et al., 2020). Emerging ideas include Transcranial Magnetic Stimulation, and more specific psychological treatments like Interpersonal and Social Rhythm Therapy (IPSRT). My conversations with psychiatry-technology enthusiasts hope for a day where we can tangibly graph the presence of mania through a combination of blood-based biomarkers, enabling episode prediction, fine-tuning of treatment, and ultimately better understanding of these human conditions.
Until that day, we can only continue to wade through the fog of clinical diagnoses, and do what we can with the treatments that we have.
P.S. I’d love to hear what you found interesting, and what you’d like more of in the comments.
Dear Dr Kevin Yu Chen Hou , I would be ever so interested in your evaluation of Dr Nial Mclarens posts on Critical Psychiatry. (Subtract). A Psychiatrist who has practiced for many decades in the specialty of Psychiatry. In the most isolated and remote parts of outback Australia (face to face). In addition to holding senior roles at leading teaching hospitals. Published author, speaker, many submissions to Australian Senate enquiries. Look forward to your next post- I think you are on the right track.